

Contents13 sections
You hit your protein goal, kept your steps up and held calories tight. Then late-night hunger wrecks the plan. Often that is less a discipline problem than a weak fullness signal between your gut and your brain.
Oleoylethanolamide (OEA) is a fat-derived messenger made in your small intestine. It helps you feel full sooner and stay satisfied longer between meals, and it acts on PPAR-alpha, a receptor that shapes how the body uses fat for energy.
Human research is early. A handful of small trials report lower hunger and small drops in weight and waist size over 8-12 weeks, mostly alongside a calorie-controlled diet. This guide covers what those trials found, the doses they used, a simple way to test OEA and the safety points that matter.
OEA is not a magic pill. It works best on top of the basics: high-protein meals, fiber, daily steps and strength training.
Key Takeaways
- OEA is a gut-made lipid that signals fullness and activates PPAR-alpha, which can make a calorie deficit easier to keep.
- Results depend on the basics: high protein, fiber, daily steps and steady strength training.
- Published human trials used 250 mg a day for 8-12 weeks. That is a dose used in studies, not medical advice.
- Trial results are modest: less hunger and small drops in weight and waist, better oxidative stress markers, and mixed effects on inflammation markers.
- If hunger does not drop after a fair trial, or side effects appear, stop and reassess with a clinician.
What Is OEA?
Oleoylethanolamide is a bioactive lipid that the small intestine makes from oleic acid, the main fat in olive oil. Gut levels rise after you eat and fall when you fast. OEA acts locally in the gut and signals the brain through the gut-brain axis, which is why researchers study it for appetite control and body weight.

Its core mechanism is activation of PPAR-alpha (peroxisome proliferator-activated receptor alpha), a receptor that switches on fat-burning genes. In simple terms, OEA nudges the body to use fatty acids for energy instead of storing them.
Key pathways at a glance:
- OEA activates PPAR-alpha and supports fatty acid oxidation.
- OEA stimulates lipolysis (fat breakdown) in fat tissue, shown mainly in animal and cell studies.
- OEA lowered some inflammation and oxidative stress markers in animals and in small trials in obese adults, including people with newly diagnosed fatty liver disease (NAFLD).
- OEA may influence gut microbiota and gut motility on a high-fat diet (animal data).
How OEA Works Through the Gut-Brain Axis

OEA adjusts hunger signals in the gut and brain, shifts how the body uses fatty acids, and may calm low-grade inflammation. Together these changes can make a calorie deficit easier to hold.
Appetite and Fullness
OEA forms in the small intestine when you eat dietary fat, especially oleic acid. It signals fullness, so you tend to stop sooner and wait longer before the next meal. In animal studies the signal travels along sensory fibers of the vagus nerve to the brain areas that control appetite, including the hypothalamus, and in rats OEA mainly lengthens the gap between meals rather than shrinking meal size. Research also notes effects on gut motility and gut microbiota, which influence food intake.
PPAR-Alpha and Fat Use
OEA activates PPAR-α. This supports fatty acid oxidation and lipid metabolism, so the body burns more fatty acids for energy and stores less. Animal work shows OEA also stimulates lipolysis in fat tissue through the same receptor, and mice that lack PPAR-α do not respond to OEA’s effects on appetite and weight.
Inflammation and Oxidative Stress
Chronic inflammation and oxidative stress go hand in hand with obesity and insulin resistance. In obesity models and some small trials, OEA lowered inflammatory markers such as tumor necrosis factor-alpha (TNF-α) and improved oxidative stress markers, with lower lipid peroxidation and higher antioxidant enzymes. Some studies also point to better insulin sensitivity. In people, these effects are smaller and less consistent than in animals.
What OEA Does Not Do
OEA is not a stimulant or a stand-alone fat burner. It will not fix a high-calorie diet or poor sleep. Think of it as an appetite and metabolism helper: the results still come from protein-forward meals, steps and strength training.
Quick Cause and Effect
| What changes with OEA | Primary effect | Why it matters for weight loss |
|---|---|---|
| Stronger gut-brain fullness signal | Earlier fullness and longer gaps between meals | Fewer calories with less hunger and fewer cravings |
| PPAR-α activation | More fatty acid oxidation | More fat used for energy, less stored |
| Lower inflammation and oxidative stress (mostly animal data) | Possible gains in insulin sensitivity | Better metabolic health while dieting |
| Consistent habits plus OEA | Less hunger and a gradual change in weight and waist | A steady calorie deficit feels easier to keep |
What the Research Says
Human data is small but growing. The published trials gave 250 mg of OEA a day for 8-12 weeks, mostly to adults with obesity or fatty liver disease, and usually alongside a calorie-controlled diet. They report less hunger and small but measurable changes in body weight, waist size and fat mass. Oxidative stress markers improved fairly consistently; effects on inflammation markers were mixed.
Key Human Trials
| Study and population | Dose and duration | Main outcomes |
|---|---|---|
| Obese adults (RCT) | 250 mg/day, 8 weeks | Lower hunger, body weight, BMI and waist than placebo; higher PPAR-α expression. A related report from the same team described lower inflammation and oxidative stress markers. |
| Obese adults with newly diagnosed NAFLD (triple-blind RCT) | 250 mg/day plus a calorie deficit, 12 weeks | Body measurements and metabolic markers improved. Liver fat trends favored OEA but were not significant between groups. |
| Obese NAFLD patients on a low-calorie diet (RCT) | 250 mg/day, 12 weeks | Higher antioxidant enzymes and lower lipid peroxidation; no between-group change in TNF-α, IL-6 or hs-CRP. |
Keep the limits in mind. These are small, short trials from a few research teams, and most paired OEA with a diet, so the extra effect of OEA itself is small. Expect earlier fullness and fewer cravings first; weight changes are modest. Larger, independent trials are still missing, and any pooled analysis can only be as strong as the small trials it combines.
Animal and Early Research
Most of this comes from animal and cell studies, so it explains the mechanism rather than proving a benefit in people.
- Diet-induced obesity: in mice fed obesogenic diets, OEA improved lipid metabolism and lowered oxidative stress, with higher antioxidant enzymes and less lipid peroxidation.
- Inflammation and immune cells: studies track immune responses and cytokines such as TNF-α, and several report anti-inflammatory effects after OEA treatment.
These signals fit the known biology of the PPAR pathway, but they still need confirmation in human trials.
OEA Dosage and Timing
Human trials gave 250 mg of OEA a day, typically as two 125 mg capsules. That is a dose used in studies, not a medical recommendation, and product strengths vary. A commonly reported approach is to start at the lower end, watch how hunger changes for one to two weeks, and stay within the studied range unless a clinician advises otherwise.
Timing and Food
Users commonly take OEA with water 30-45 minutes before a meal, often the largest one, or split it before lunch and dinner if late-day cravings are the problem. Some people prefer a little healthy fat in the meal for stomach comfort. Give any pattern at least four weeks.
Forms and Labels
OEA comes as capsules and as raw powder. Choose a product that lists the exact milligrams of OEA per serving, ideally with third-party testing or a certificate of analysis and few added fillers. Avoid blends that hide the dose. Supplements are not checked by the FDA before they are sold, so testing matters.

Pros
- Exceptional purity & testing (≥98%)
- Pharmaceutical-style packaging for stability
- Broad catalog across peptides & nootropics
- Strong reputation & consistency across years
Cons
- Some items frequently out of stock due to high demand
- Limited long-term data for some compounds
A 4-Week Trial Protocol
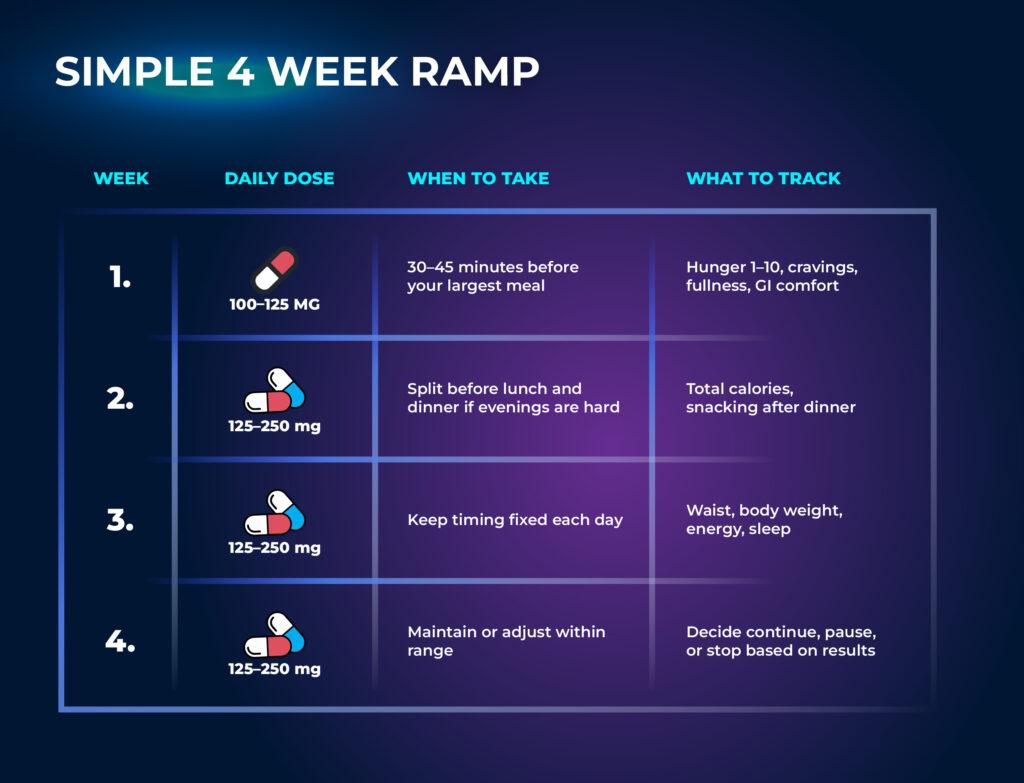
Use this four-week plan to test whether OEA helps you control appetite during a cut. Stay inside the doses used in studies, and pair it with protein-forward meals, steps and strength work.
| Week | Commonly reported dose | Focus |
|---|---|---|
| Week 1 | 100-125 mg a day, 30-45 minutes before the largest meal | Rate hunger before and after meals on a 1-10 scale. Hit your protein target, keep steps high and note stomach comfort. |
| Week 2 | Up to 250 mg a day if appetite control is still weak, split before lunch and dinner | Keep calories steady and add fiber and water. Watch weight, cravings and sleep. |
| Week 3 | Hold the dose | Train 2-4 days a week and keep steps consistent. Record waist, body fat trend and energy. If you get blood work, note fasting glucose. |
| Week 4 | Hold, pause or stop | Review the data: look for a clear drop in hunger and snacking and a small change in weight and waist. |
Decision Guide
Continue if hunger drops by 2 or more points, snacking falls and weight trends down about 0.3-0.7% a week. Stop if nothing changes or side effects appear. If you have metabolic syndrome or take several medications, involve a clinician.
What to Track
- Hunger ratings, meal size and food intake
- Body weight, waist and a simple body composition estimate
- Energy, sleep and training volume
- Side effects, stomach comfort and adherence
Stacking OEA With Diet, Training and Caffeine
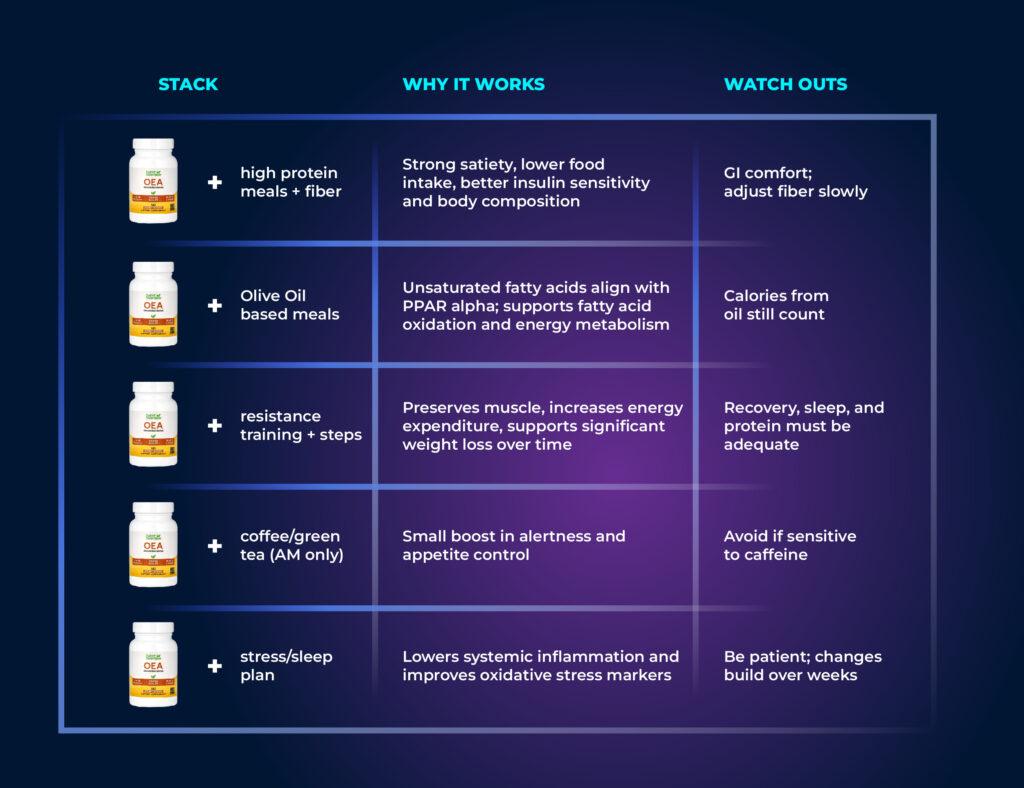
Most of these pairings have not been tested with OEA in trials; they are standard fat-loss habits that fit what it does.
Diet: Protein, Fiber and Healthy Fats
Build meals around protein, fiber and healthy fats. Oleic acid, the fat your gut turns into OEA, is plentiful in olive oil, avocado and nuts.
- Anchor each meal with 25-40 g of protein.
- Add high-fiber vegetables and fruit.
- Use olive oil or avocado for healthy fats.
- Drink water before meals to help lower food intake.
Why it helps: protein and fiber raise fullness signals on their own, and oleic acid is the raw material for the OEA your gut makes.
Training
Lift 2-4 days a week and keep daily steps high. Resistance training preserves muscle while you lose fat, and steps raise energy expenditure without heavy fatigue. Look for a smaller waist with stable strength.
Caffeine and Green Tea (Optional)
You can pair OEA with coffee or green tea for gentle appetite control and a small lift in energy expenditure. Start small and avoid late-day use. Skip heavy stimulant stacks, and watch sleep, heart rate and stress: poor sleep drives hunger and blunts fat loss.
With GLP-1 Medications
Some people on prescription semaglutide or similar drugs ask about OEA. There are no trials of the combination, and both reduce appetite, so intake can drop too low. Discuss it with the prescribing clinician first.
Sleep and Stress
Habits that lower inflammation support the same goals: 7-9 hours of sleep, stress management and plenty of colorful plants, which supply dietary antioxidants. Short sleep and chronic stress both push hunger up; if stress is your weak spot, see our guide to supplements that lower cortisol.
Who Might Benefit Most (and Who Should Skip)

OEA is most likely to help if hunger is the main thing breaking your calorie deficit: portions creep up and late-night cravings make you overshoot. People with obesity or insulin resistance who are under medical care can raise it with their clinician.
Signs you are a good fit
- Strong appetite on a cut despite solid protein and fiber
- High-calorie environments at work or home
- Late-night snacking that breaks the plan
- Elevated body weight or BMI within a supervised program
Use With Care
Talk to your clinician first if you take drugs for blood lipids, blood sugar or appetite, or live with metabolic syndrome, cardiovascular disease or an active inflammatory condition.
Who Should Skip for Now
- Pregnancy or breastfeeding
- Active stomach, bowel, liver or gallbladder disease, or a history of acute liver injury
- A recent stroke or a complex medication routine
- Allergies or sensitivities to supplement ingredients
- Anyone a clinician has advised to avoid appetite-reducing agents
Safety, Side Effects and Interactions
The published trials were small and short, so long-term safety is not established. Bodies respond differently: start low, track your own response, and never replace medical care with supplements.
Common Side Effects
Reported side effects are mostly digestive: nausea, reflux or stomach discomfort. Some people notice headaches or lighter sleep when they combine OEA with caffeine. Lower the dose or take it earlier in the day if this happens; if symptoms persist, stop and speak with a clinician. Do not use OEA during pregnancy or breastfeeding without medical advice.
Possible Drug Interactions
- Lipid-altering drugs: fibrates also act on PPAR-alpha, and the pathways overlap in fat metabolism. Coordinate with your clinician.
- GLP-1 or other appetite drugs: combined use can push appetite too low. Monitor food intake and energy.
- Stimulants: caffeine or strong pre-workouts may worsen reflux or sleep. Keep doses modest and earlier in the day.
Red Flags
Stop and seek medical advice for severe or persistent stomach pain, vomiting, rapid unintended weight loss, or signs that you are eating far too little. Anti-inflammatory signals from small studies do not replace medical care.
Comparing OEA to Other Weight Loss Aids
OEA sits in the non-stimulant space: its main effect is appetite control. Stimulants cut appetite fast but can disrupt sleep, prescription drugs are far stronger but need medical oversight, and fiber is simple and safe but slower.
| Option | How it works | Pros | Watch outs |
|---|---|---|---|
| OEA (non-stimulant) | Signals fullness and activates PPAR-α to support fat use | Calmer appetite without jitters | Small human evidence base; track stomach comfort; pair with diet and training |
| Caffeine and similar stimulants | Boost alertness and can blunt appetite short term | Fast effect, easy access | Sleep problems, higher stress, tolerance |
| Fiber supplements (psyllium, glucomannan) | Slow gastric emptying and increase fullness | Safe; also helps blood lipids and blood sugar | Bloating if added too fast; needs plenty of water |
| Green tea extract | Mild appetite and metabolic support | Gentle, widely used | Nausea or poor sleep in sensitive users; high-dose extracts have been linked to rare liver injury |
| Orlistat | Blocks fat absorption in the gut | Modest weight loss alongside a diet | GI side effects, loss of fat-soluble vitamins; best used with medical advice |
| GLP-1 medications | Slow gastric emptying and reduce hunger signals | Strong appetite control, large weight loss in trials | Prescription and follow-up needed; GI side effects are common |
Where OEA Fits
OEA gives appetite control without a stimulant load and fits cleanly with protein-forward meals and steps. Its effects on insulin sensitivity look promising in animals but are not well established in people. If hunger is extreme or metabolic disease is present, a clinician may prefer prescription options first; our guide to the best peptides for weight loss covers the GLP-1 class. Fiber works for nearly everyone and can be combined with OEA.
The Bottom Line
OEA is a real gut-brain fullness signal with a plausible mechanism, but the human evidence is small and the effects on weight are modest.
- Its main benefit is appetite control: earlier fullness and longer gaps between meals, which can make a calorie deficit easier to hold.
- Published trials used 250 mg a day for 8-12 weeks, usually with a calorie-controlled diet. Expect small changes in weight and waist, not dramatic loss.
- Run a measured four-week trial and track hunger, snacking, weight and waist. Keep going if they improve; stop after 8-12 weeks with no change, or as soon as side effects appear.
- Protein, fiber, steps, strength training and sleep do most of the work. OEA is a helper, not a replacement.
Frequently Asked Questions
Disclaimer
Please read carefully
The information on this site is for educational and informational purposes only, and is not medical advice. Always consult a qualified healthcare professional before using any supplement or medication, or making changes to your health, fitness, or nutrition routine.
Not medical advice
Content here is not a substitute for professional medical advice.
Consult your doctor
Talk to your doctor before starting any supplement or new routine.
Use at your own risk
We are not responsible for adverse effects from acting on this.
Do your research
Make informed decisions about your own health.
No guarantees
Individual results vary. No claims about outcomes.
Important — Never disregard professional medical advice or delay seeking it because of something you read here. If you think you may have a medical emergency, call your doctor or your local emergency number right away.


