

Contents13 sections
Men need some estrogen. Estradiol (E2), the main estrogen, helps keep bones strong and supports sex drive and erections. But when it climbs too high on testosterone replacement therapy (TRT), it can cause water retention, nipple tenderness and even breast tissue growth (gynecomastia).
Testosterone is the raw material for estradiol. The aromatase enzyme converts one into the other, so raising testosterone usually raises E2 as well. Most men on standard TRT doses never develop high estradiol levels, but men with more body fat, older men and men on higher doses are more likely to.
This guide covers what estrogen does in men, what drives it up, the symptoms and blood tests that matter, and the options a doctor may use, from fat loss and dose changes to aromatase inhibitors (AIs) and SERMs. In short, the best way to control estradiol on TRT is usually the simplest one: get the testosterone dose right, lose excess body fat, and keep medication for confirmed high E2 that is causing symptoms.
Key Takeaways
- TRT usually raises estradiol (E2), because the aromatase enzyme converts testosterone into estrogen. The rise follows the testosterone dose and is larger in men with more body fat.
- Clearly high E2 is uncommon on standard TRT doses. When it happens, it can cause water retention, nipple tenderness or gynecomastia in susceptible men.
- The symptoms overlap with low testosterone and other problems, so confirm with a sensitive estradiol blood test before changing anything.
- The first steps are usually losing excess body fat and fixing the testosterone dose or injection schedule. Routine aromatase inhibitor use with TRT is not recommended.
- Anastrozole and tamoxifen are prescription drugs. Used without blood work, an AI can crash E2 and cause joint pain, low libido and bone loss.
What Is Estrogen?
Estrogens are known for their feminizing effects, but men make them too, and they play an important role in male physiology. They have been known to be present in substantial amounts in men for decades, yet their exact role is still debated. [1]
Estrogen has long been known to matter for bone and blood vessel health in both sexes. Its role in sexual function, erections, sex drive and body fat is now being studied more closely, and the growing use of TRT has renewed interest in it.
Testosterone and estrogen are tightly linked: testosterone is the main source of estradiol in men, through a process called aromatization. So when TRT raises testosterone, estradiol usually rises too. That is why managing estrogen is part of good TRT care, especially for men who want the full benefit for sex drive, muscle and fat loss.
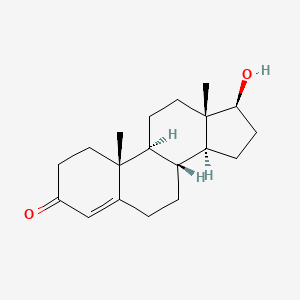
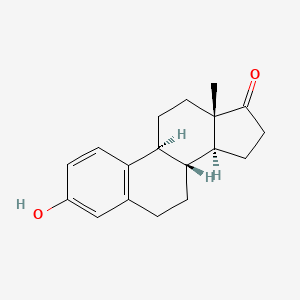
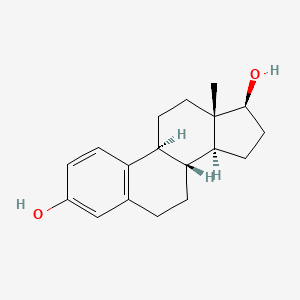
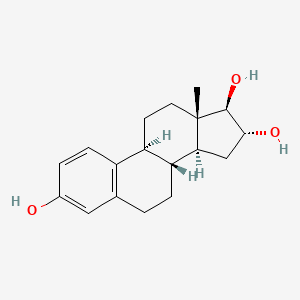
The body makes three main estrogens: estrone (E1), 17β-estradiol (E2) and estriol (E3). Of these, E2 binds estrogen receptors most strongly and is the most biologically active, which is why it is the one measured on TRT. [2]
Estrogen Production in Men
About 80% of the estradiol in a man’s blood is made outside the testes, by aromatization of testosterone in tissues such as fat. The remaining 20% or so is made directly by the Leydig cells in the testes. [1] A small amount also comes from the conversion of other androgens. [3]
As with testosterone, a large share of E2 in the blood is bound to sex hormone-binding globulin (SHBG), and this bound fraction is not considered biologically active.
Factors Affecting Estrogen Production in Men
Testosterone Levels
Because testosterone is the raw material for about 80% of serum E2, changes in testosterone levels change E2 levels too. [1] Anything that raises testosterone, TRT included, tends to raise estradiol with it. This is why controlling estradiol on TRT starts with the testosterone dose.
Body Fat and Aromatase
Fat tissue is one of the main sites of aromatase in men, so more body fat means more testosterone converted into estradiol. Multiple studies have found higher E2 levels in obese men and a direct relationship between E2 and BMI. [4]
Vermeulen et al. found that in obese men aged 30 to 60, subcutaneous fat measured by computed tomography was strongly associated with free E2, whereas abdominal fat was not. [5]
Obesity often comes with metabolic syndrome: high blood pressure, high blood sugar and abnormal cholesterol. Obese men with metabolic syndrome tend to have lower testosterone, higher estradiol and lower SHBG.
Weight loss reverses part of this. In obese men, E2 was lower two years after gastric bypass surgery while SHBG rose, which gave an even larger fall in bioavailable E2. [1] Men whose testosterone is low for their age and who start TRT while carrying a lot of body fat should expect a bigger rise in E2.
Aging
As men age, testosterone production often declines while body fat tends to increase, so the balance between estrogen and testosterone can shift toward estrogen.
Medications and Other Causes
- Antiepileptic drugs: phenytoin and carbamazepine are associated with high E2 in men with sexual dysfunction, possibly through increased aromatase activity. [1]
- Estrogen exposure: estrogen given at pharmacologic doses and, rarely, estrogen-secreting adrenal tumors lower testosterone by suppressing the pituitary hormones (gonadotropins) that drive it.
- Anabolic steroids: steroids that aromatize, such as testosterone at bodybuilding doses, can raise estrogen far above the levels seen on TRT. Non-aromatizing compounds are covered in our guide to steroids that don’t cause gyno.
Role of Estrogen in Men
Testosterone Regulation
Estrogen gives negative feedback to the brain (the hypothalamus and pituitary), reducing the release of GnRH and LH, the signals that tell the testes to make testosterone. In men who are not on TRT, high estrogen can therefore suppress natural testosterone production.
On TRT, your own production is already largely suppressed by the testosterone you take, so this feedback matters less than the direct effects of E2 on your tissues.
Bone Health
Estrogen is vital for bone health in men, and this is well studied. Longitudinal studies show that low total and bioavailable E2 levels are linked to faster bone loss, with the risk rising below a threshold of about 40 pmol/L (11 pg/mL) of bioavailable E2. [6]
Men with congenital aromatase deficiency, who cannot make estrogen, show tall stature, continued growth in height, delayed bone age and osteopenia or osteoporosis. [1] This is the main reason not to push E2 too low.
Cardiovascular Health and Metabolism
Testosterone and E2 together may help blood vessels widen normally (endothelial-dependent vasodilation) and help prevent the buildup of plaque in the arteries. Men with congenital aromatase deficiency develop features of metabolic syndrome, including abdominal fat gain and impaired insulin sensitivity. [1]
Sexual Function
Estradiol matters for sex drive and erections as well. There is some evidence that estrogens help preserve erectile function when testosterone is severely suppressed, as in men who have undergone castration for advanced prostate cancer. [1]
A controlled study by Finkelstein and colleagues, published in the New England Journal of Medicine in 2013, shut down men’s own hormone production and then gave different doses of testosterone (or placebo), with or without an aromatase inhibitor. Low estrogen was mainly responsible for the gains in body fat, and both low testosterone and low estrogen contributed to declines in sexual function. In other words, a man on TRT needs some estradiol to get the full benefit.
Symptoms of High Estrogen in Men on TRT
Possible signs that estradiol is too high on TRT include:
- Water retention, such as puffy ankles (look for sock marks)
- Puffy, sore or sensitive nipples, or a lump under the nipple
- Mood swings or unexplained emotions, such as feeling teary
- Erectile dysfunction or reduced libido
None of these is specific. Water retention, low mood and erection problems are also common with low testosterone, a dose that is too high, poor sleep or other health problems. Nipple tenderness and new breast tissue are the most telling signs. Gynecomastia is fairly common in men in general, so any lump should be checked by a doctor.
Estradiol that is too low, usually from too much aromatase inhibitor, causes its own problems, and some of them are easy to mistake for high E2:
| Often linked to high E2 | Often linked to low E2 |
|---|---|
| Water retention, puffy ankles | Joint pain or stiffness |
| Nipple tenderness or puffiness | Low libido |
| Mood swings, feeling teary | Low mood and fatigue |
| Erection problems | Erection problems |
| Breast tissue growth (gynecomastia) | Bone loss over time, often without symptoms |
Managing High Estradiol on TRT: Finding the Best Way
If you suspect high estrogen is causing problems, the first step is always to discuss your symptoms with your prescribing doctor and get blood work done. The right approach is individual, but it usually runs in this order: confirm the problem, adjust lifestyle and the TRT protocol, and only then consider medication.
Confirm It With the Right Blood Test
The upper limit of normal for E2 in men is not clinically defined. Laboratory reference ranges depend on the assay, but the upper bound is often given as about 50 pg/mL (roughly 180 pmol/L). [1]
- Ask for the sensitive estradiol test (usually run by LC-MS/MS). Standard estradiol immunoassays are designed for the higher levels seen in women and can be inaccurate at male levels.
- Test at the same point in your injection cycle each time, because E2 rises and falls with testosterone after each shot.
- Read it in context, alongside total and free testosterone and your symptoms. A high number with no symptoms is usually not treated.
Lose Excess Body Fat
Since fat tissue drives aromatization, reducing excess body fat through diet and exercise is often the most effective natural way to lower E2. It also improves the metabolic problems that tend to travel with high estrogen.
Optimize the TRT Protocol
If your testosterone is running above the normal range, lowering the dose usually brings E2 down with it. Splitting the same weekly dose into smaller, more frequent injections can also give steadier levels and lower E2 peaks. Our TRT dosage calculator shows how doses and schedules compare. Discuss any change with your doctor.
Pharmaceutical Options (Use With Caution and Medical Guidance)
When lifestyle and dose changes are not enough, and symptoms persist alongside confirmed high E2 levels, medication may be the next step, under medical supervision.
Aromatase Inhibitors (AIs)
AIs block the aromatase enzyme, which converts testosterone into estradiol (and androstenedione into estrone). The enzyme is found in the testes, brain, fat tissue, bone, muscle, hair and blood vessels. Blocking it lowers estradiol directly, which makes AIs potent estrogen blockers.
An AI does not “stop the breakdown of testosterone”. It blocks one conversion step, so less testosterone becomes estradiol. In men who are not on TRT, the weaker estrogen feedback lets the pituitary release more LH, so their own testosterone rises. In men on TRT, whose own production is already suppressed, the main effect is simply lower E2.
The most commonly discussed AI is anastrozole (brand name Arimidex), a third-generation, non-steroidal AI that binds aromatase reversibly. Steroidal AIs such as exemestane bind the enzyme irreversibly and are used less often in men on TRT.
Anastrozole is used alongside TRT in some clinics, but it should be approached cautiously. It lowers E2 effectively, but it can also crash levels too low if it is not dosed carefully, leading to joint pain, low libido and, over time, poorer bone health. Routine AI use with TRT is generally not recommended by mainstream medical guidelines unless clear symptoms and significantly elevated E2 levels are present.
Get it through the prescription route. Anastrozole is a prescription medicine. If your doctor decides an AI is warranted, it should come the same way as your testosterone: prescribed, dispensed by a licensed pharmacy and dosed from your blood work, with E2 rechecked after any change. “Research chemical” anastrozole bought online skips the testing that tells you whether you need it at all, and its strength and purity are not regulated. If your current provider does not monitor estradiol properly, a reputable TRT clinic can; see our comparison of the best online TRT clinics.

Pros
- LegitScript-certified telehealth provider that uses licensed U.S. pharmacies.
- Licensed providers review every intake, and TRT plans include quarterly bloodwork.
- Direct-pay pricing with the consultation and shipping included and no membership fees.
- Fully remote, with no clinic visits and treatments shipped to your door.
Cons
- Serves U.S. patients only.
- Some treatments are compounded and have not been evaluated by the FDA for safety or effectiveness.
Off-label, AIs have also been used instead of TRT in some men with low testosterone and relatively high estradiol, for example men with obesity or infertility, because they raise the body’s own testosterone without suppressing sperm production. This is not an approved use. Some clinicians also use anastrozole for gynecomastia, although tamoxifen has stronger evidence for breast symptoms.
Selective Estrogen Receptor Modulators (SERMs)
SERMs don’t lower overall estrogen levels like AIs. Instead, they block estrogen receptors in some tissues (like the breast) while acting like estrogen in others (like bone). They are not a first-line way to lower systemic E2 on TRT, but they are used for specific problems such as gynecomastia.
Tamoxifen and clomiphene are both SERMs. They and their metabolites change the shape of the estrogen receptor and selectively alter the signal it sends. [1]
Tamoxifen (Nolvadex)
Tamoxifen (Nolvadex) is used off-label to treat or prevent gynecomastia in men, including men on TRT who develop breast tenderness or tissue growth, because it blocks estrogen at the breast. It can also reduce bone turnover and increase bone mineral density. In men who are not on TRT, it can raise testosterone and may help in the treatment of male infertility. [1]
Like anastrozole, tamoxifen is a prescription drug. Any use should go through your doctor, who can also rule out other causes of breast enlargement.
Clomiphene: An Alternative to TRT, Not an E2 Fix
Clomiphene citrate (Clomid) blocks estrogen receptors in the hypothalamus and pituitary, which increases the release of GnRH, LH and FSH and so boosts the body’s own testosterone. [7] It is not typically used alongside TRT to control E2.
Instead, it is used off-label in place of TRT, particularly when a man wants to keep his fertility, because unlike TRT it does not reduce gonadotropins or sperm concentration. [1] It has been used to treat infertility for over 50 years, mainly in women. [7] In men with low testosterone, studies have reported:
- Testosterone levels comparable to those reached with testosterone gels [8]
- Higher testosterone without changes in prostate-specific antigen (PSA) or hematocrit [9]
- Better erectile function in men with secondary testosterone deficiency [10]
- Similar improvement in symptom scores (ADAM) compared with topical testosterone, in a nonrandomized study [11]
Clomiphene is also a less expensive alternative to testosterone replacement. [7] For a fuller comparison, see enclomiphene vs TRT.
Natural Support Options for Estradiol on TRT
Several supplements are marketed as natural estrogen blockers, but none has good evidence for lowering E2 in men on TRT. Here is what is known about the most common ones:
- DIM (diindolylmethane): formed from compounds in cruciferous vegetables such as broccoli, DIM may shift how estrogen is metabolized. Most of the research is in lab studies and in women, and there is no good evidence that it lowers estradiol in men on TRT.
- Calcium D-glucarate: sold to support how the body clears estrogen. Human evidence that it changes estradiol levels is lacking, and ordinary calcium supplements do not lower estrogen.
- Zinc: adequate zinc matters for testosterone production, and correcting a deficiency can help. There is no good evidence that extra zinc lowers estradiol in men who already get enough.
Body fat, the testosterone dose and the injection schedule will move your E2 far more than any supplement.
Estrogen Response to TRT
Lakshman et al. studied how estradiol responds to testosterone in a group of young men and a group of older men. Both total and free E2 rose with testosterone, and older men converted more testosterone into estradiol, which was explained by their greater fat mass. [1]
These results suggest that TRT raises serum E2, with possibly greater increases in older or obese men. Injectable TRT, such as testosterone cypionate or enanthate, tends to raise estradiol more than other forms, because testosterone peaks in the days after each injection. See our comparison of testosterone gel vs injection.
Elevated E2 During TRT: To Treat or Not to Treat?
TRT may raise serum E2, in some cases above the upper limit of normal, and nipple or breast tenderness or gynecomastia has been reported with TRT. In these cases, there is a clear reason to lower E2. Some authors recommend stopping TRT first until the symptoms resolve, then restarting it together with an aromatase inhibitor. [1]
Some clinicians, particularly in the anti-aging field, give an AI routinely with TRT even when there are no symptoms of estrogen excess, believing that keeping estrogen low improves men’s health and the results of TRT. The evidence does not support this.
The authors of the 2012 review on estrogens in men concluded that: [1]
- Naturally occurring rises in E2 do not appear to harm testosterone levels or sexual function.
- E2 may increase on TRT, but levels above the normal range are uncommon, and they may settle with longer treatment.
- Symptoms of estrogen excess, such as gynecomastia or nipple tenderness, are rare. Men who get them should consider stopping TRT for a while or for good, or adding an aromatase inhibitor.
- Routine AI use with TRT is not recommended. Men who are doing well on TRT without signs of estrogen excess have no reason to take an AI, even if their E2 is high-normal or elevated.
- When an AI is used, it should be adjusted so that E2 stays above about 40 pmol/L to protect bone, with bone density monitored by DXA scan.
Current practice follows the same line: mainstream guidelines do not recommend routine AI use on TRT, and estradiol is usually checked when breast symptoms appear rather than as a routine test.
The Bottom Line
The best way to control estradiol on TRT is usually not a pill: get the testosterone dose right, lose excess body fat, and treat E2 only when a reliable blood test and real symptoms both point to it.
- Some rise in E2 on TRT is normal, and men need estradiol for bone, sex drive and erections. Clearly high E2 with symptoms is uncommon on standard doses.
- Confirm with a sensitive estradiol test, taken at the same point in your injection cycle, before changing anything.
- If medication is needed, anastrozole or tamoxifen should come from your prescriber and a pharmacy, dosed to your labs. Crashing E2 harms bones, joints and sex drive.
Frequently Asked Questions
Disclaimer
Please read carefully
The information on this site is for educational and informational purposes only, and is not medical advice. Always consult a qualified healthcare professional before using any supplement or medication, or making changes to your health, fitness, or nutrition routine.
Not medical advice
Content here is not a substitute for professional medical advice.
Consult your doctor
Talk to your doctor before starting any supplement or new routine.
Use at your own risk
We are not responsible for adverse effects from acting on this.
Do your research
Make informed decisions about your own health.
No guarantees
Individual results vary. No claims about outcomes.
Important — Never disregard professional medical advice or delay seeking it because of something you read here. If you think you may have a medical emergency, call your doctor or your local emergency number right away.




