

Contents16 sections
Everything in the nootropic space gets called a cognitive enhancer, and every compound is said to improve memory, focus and mental clarity. After a while the claims blur together, and it becomes hard to tell what separates one compound from another, or whether any of them is worth considering.
The compounds in this category are not interchangeable. Piracetam and Dihexa are both called nootropics, but they work through different mechanisms and have evidence bases that look nothing alike: piracetam has been tested in people for decades, while Dihexa has only been studied in cells and animals.
This guide covers eight of them, ranked by the strength of their human evidence rather than by marketing appeal. For each one you’ll find what it is, how it is thought to work, what the human studies show, the doses used in those studies (or the fact that there are none), and the main safety questions. Most of these compounds are subtle at best, and none of them is approved by the FDA.
Key Takeaways
- Piracetam has the longest human research record of the eight, but trial results in cognitive impairment are mixed and there is little good evidence that it helps healthy adults.
- None of the eight compounds is FDA-approved, and none can legally be sold as a dietary supplement in the US. Piracetam is a licensed medicine in a number of European countries.
- NSI-189 was tested in depression, not as a cognitive enhancer: its Phase 2 trial missed its primary endpoint, and no study has measured neurogenesis in people.
- 9-Me-BC and Dihexa have no human data at all. Everything known about them comes from cell and animal studies, so there is no studied human dose.
- Most dosing, stacking and choline advice for these compounds comes from user reports, not trials. If you research them, ask for a certificate of analysis for your exact lot first.
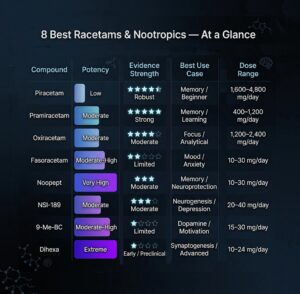
8 Best Racetams and Nootropics at a Glance
The table lists the eight in order of how much human evidence stands behind them. A “studied” dose is one tested in published human trials; a “reported” dose is what users commonly describe, which is not advice. Where no human data exist, the table says so.
| Compound | What It Is | Human Evidence | Studied or Reported Dose |
|---|---|---|---|
| Piracetam | Racetam | Many trials in cognitive impairment, stroke and myoclonus; mixed results | Studied: typically 2.4–4.8 g/day in cognitive trials; up to 24 g/day for myoclonus |
| Pramiracetam | Racetam | A few small, older trials | Reported: 400–1,200 mg/day |
| Oxiracetam | Racetam | Small dementia trials; mixed results | Reported: 1,200–2,400 mg/day |
| Fasoracetam | Racetam | Dropped for dementia; one small early ADHD trial | Studied: 50–400 mg twice daily (ADHD trial) |
| Noopept | Dipeptide, not a racetam | Small Russian clinical studies | Studied: 20 mg/day (10 mg twice daily) |
| NSI-189 | Experimental antidepressant candidate | Phase 1b and Phase 2 trials in depression; Phase 2 missed its primary endpoint | Studied: 40–120 mg/day |
| 9-Me-BC | Beta-carboline | None (cell and rat studies only) | No human data |
| Dihexa | Angiotensin IV analogue | None (cell and rodent studies only) | No human data |
1. Piracetam: The Best-Studied Starting Point
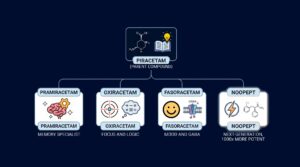
Piracetam is the most studied compound in the category and the one every other racetam is compared with. It was first made at UCB in Belgium in 1964, and Corneliu Giurgea, the Romanian scientist behind its development, coined the word “nootropic” in 1972 to describe a compound that improves learning and memory without sedating or stimulating.
It has been tested in people with age-related cognitive decline, dementia, stroke, dyslexia and sickle cell disease. The results are mixed: some trials in older adults with cognitive impairment reported benefits, large stroke trials did not show a clear effect on their main outcome, and there is little good evidence that it improves cognition in healthy adults. In the UK, for example, it is licensed only for cortical myoclonus, a movement disorder.
How It Works
Its mechanism is still not fully settled. Lab work shows it acts as a weak positive modulator of AMPA receptors, which carry the fast glutamate signalling involved in learning. Animal studies also point to effects on acetylcholine signalling in the hippocampus, on the fluidity of nerve cell membranes, and on blood flow and platelet function.
Piracetam produces no noticeable effect from a single dose. In trials, any benefit was measured over weeks of daily use, which is why people who expect to feel something in the first few days usually conclude it does nothing.
What People Use It For
People new to racetams often start here because piracetam has the longest safety record and the most predictable profile. Most of the clinical trials were run in older adults with memory problems, which is also the group in which benefits were most often reported.
Doses Used in Studies and Safety
Trials in cognitive impairment typically used 2.4 to 4.8 g a day, split into two or three doses. The European label for cortical myoclonus allows up to 24 g a day under medical supervision. Commonly reported doses among nootropic users fall in a similar range, about 1.6 to 4.8 g a day.
In trials it was generally well tolerated; reported side effects include nervousness, agitation, weight gain and drowsiness. It is cleared by the kidneys and affects platelet function, so its European label warns about kidney disease and bleeding risk. Many users add a choline source to avoid headaches; that practice comes from user reports, not from trials.
2. Pramiracetam: The Memory-Focused Racetam
Pramiracetam was developed by Parke-Davis in the late 1970s and was later sold in Italy, under the brand name Pramistar, for memory problems in older adults. It is dosed in hundreds of milligrams rather than grams, and users usually describe it as the most memory-focused of the classic racetams.
Its human evidence is thin: a handful of small trials, mostly from the 1980s and early 1990s, in older adults with memory problems and in young men with memory difficulties after head injury. Reports that its memory effect is sharper than piracetam’s come from users, not from head-to-head trials.
How It Works
In rat studies, pramiracetam increased high-affinity choline uptake in the hippocampus. That is the rate-limiting step in making acetylcholine, the neurotransmitter most closely tied to forming new memories. Users report little direct effect on mood, which is one reason it is often described as a neutral compound to combine with others.
What People Use It For
Students and professionals who need to learn large amounts of material, and users who found piracetam too mild.
Doses
There is no well-established human dose. Commonly reported doses are 400 to 1,200 mg a day, split into two doses and usually taken with a meal. The small clinical trials do not establish a dose or long-term safety for healthy adults.
3. Oxiracetam: The One Users Pick for Analytical Work
Oxiracetam was developed in Italy in the 1970s and studied through the 1980s and 1990s in dementia and other cognitive disorders, with mixed results in mostly small trials. It is the racetam users most often describe as mildly activating: not a stimulant in the caffeine sense, but a sharper focus they find suits logical, mathematical and technical work.
How It Works
In animal and lab studies, oxiracetam enhanced AMPA-type glutamate signalling and affected acetylcholine and D-aspartate release in the hippocampus. These are proposed mechanisms from animal work; none has been confirmed in people, and the “activating” quality is a user description rather than a measured effect.
What People Use It For
Sustained analytical work such as programming, maths and study. Because users describe it as activating, it is usually taken earlier in the day, and people who are already prone to overstimulation tend to avoid it.
Doses
Commonly reported doses are 1,200 to 2,400 mg a day, split between morning and early afternoon. The dementia trials used doses in a similar range in older patients; there is no studied dose for healthy adults.
4. Fasoracetam: Studied for Dementia, Then ADHD
Fasoracetam (NS-105) was developed in Japan by Nippon Shinyaku in the 1990s for vascular dementia, and development for that use was dropped. It later returned as a candidate ADHD treatment for adolescents who carry variants in genes of the metabotropic glutamate receptor (mGluR) network.
In a small, five-week early-phase trial in 30 adolescents with ADHD and these gene variants (Elia et al., Nature Communications, 2018), symptoms improved at doses escalating from 50 mg to 400 mg twice daily. It was a small, short trial, and its result has not been confirmed in a larger controlled study.
How It Works
In rat studies, fasoracetam activated metabotropic glutamate receptors, increased the number of GABA-B receptors after repeated dosing, and increased high-affinity choline uptake. GABA-B receptors are inhibitory, which is the basis for user reports that fasoracetam gives calmer focus than more activating racetams. That calming effect has not been tested in human trials.
Claims that fasoracetam “resets” tolerance to other racetams have no published evidence behind them.
What People Use It For
Users who find that other racetams make them anxious or wired, and people interested in its ADHD research. ADHD has approved, well-studied treatments; fasoracetam is not one of them.
Doses
The only modern human dosing data come from the ADHD trial above, in adolescents under medical supervision. The doses commonly reported online are far lower, typically 10 to 30 mg a day, and are not based on any study.
5. Noopept (Omberacetam): Not Technically a Racetam
Noopept is grouped with racetams because its uses overlap, but chemically it is a synthetic dipeptide: it lacks the pyrrolidone ring that defines the racetam class. It was developed in Russia in the 1990s and is registered there as a medicine for cognitive disorders. It is dosed in milligrams rather than grams; the popular claim that it is “1,000 times more potent than piracetam” comes from animal comparisons of effective doses, not from human trials.
How It Works
After it is absorbed, Noopept is broken down into cycloprolylglycine, a peptide the brain makes naturally, which has shown anti-anxiety and protective effects in animal studies. In rats, Noopept increased the expression of BDNF and NGF in the hippocampus. These two growth factors support the survival and plasticity of neurons. They are animal findings; they have not been measured in people.
What People Use It For
Users who want racetam-like effects on memory and focus at a milligram dose, and people who have tried piracetam and want something with a different mechanism.
Doses Used in Studies
Russian clinical studies in patients with mild cognitive problems after vascular disease or brain injury used 20 mg a day, taken as 10 mg twice daily, which is also the usual dose on the Russian label. Those studies were small, and there are no large placebo-controlled trials. Commonly reported doses among users are 10 to 30 mg a day; the cycling schedules seen online come from user practice, not research.
6. NSI-189: Studied for Depression, Not Neurogenesis in People
NSI-189 is not a racetam. Neuralstem developed it as a treatment for major depression after screening compounds for their ability to stimulate new neurons in lab-grown human hippocampal stem cells. In mice it increased hippocampal neurogenesis and hippocampal volume. That is where the “neurogenesis compound” label comes from, and it is lab and animal data only.
The human trials tell a more modest story:
- Phase 1b (Fava et al., Molecular Psychiatry, 2016): 24 patients with major depression, not healthy volunteers, took 40 mg once, twice or three times a day, or placebo, for 28 days. It was a small safety study. The treated groups improved on some depression and cognitive scales, but the trial was too small to show efficacy, and no neurogenesis was measured.
- Phase 2 (Papakostas et al., Molecular Psychiatry, 2020): about 220 outpatients with major depression took 40 mg or 80 mg a day, or placebo, for 12 weeks. It missed its primary endpoint, the clinician-rated depression score. Some secondary measures, including some cognitive tests, favoured the 40 mg dose, but secondary results from a trial that missed its main goal are exploratory.
So NSI-189 has been tested in people with depression at 40 to 120 mg a day. It has not been shown to grow new brain tissue in humans, and it has not been tested as a cognitive enhancer in healthy people.
How It Works
In lab and mouse studies, NSI-189 stimulated the growth of neural stem cells in the hippocampus, the brain region most involved in memory and spatial navigation and one that tends to shrink in chronic depression. The exact mechanism has not been worked out. Whatever it does, it produces no acute effect: the trials measured change over four to twelve weeks.
Doses Used in Studies
40, 80 and 120 mg a day for 28 days in the Phase 1b trial, and 40 or 80 mg a day for 12 weeks in Phase 2, all in people with depression. There is no studied dose for healthy users, and safety data beyond twelve weeks are lacking. Depression and the cognitive problems that come with it are best treated with a doctor, using approved options.
7. 9-Me-BC: The Dopaminergic One (Animal Data Only)
9-Methyl-beta-carboline (9-Me-BC) works on the dopamine system rather than the glutamate and acetylcholine systems targeted by racetams. That is why it is discussed for motivation and drive rather than memory. There are no human studies of it at all.
How It Works
In cell cultures, 9-Me-BC increased the number and branching of dopamine-producing neurons and the expression of tyrosine hydroxylase, the enzyme that limits how much dopamine is made (Hamann et al., Neurochemistry International, 2008). It also inhibits MAO-A and MAO-B, the enzymes that break dopamine down, and raised the production of nerve growth factors in lab studies.
In rats, it improved spatial learning and raised dopamine levels in the hippocampus (Gruss et al., Journal of Neurochemistry, 2012), and in rat models of Parkinson’s disease it had restorative effects on damaged dopamine neurons. User reports describe a gradual return of motivation rather than an acute lift, but there is no human trial to check that against.
Doses and Safety
No human data. There is no studied human dose, and the doses circulating online are anecdotal. Its MAO-inhibiting activity is the main known concern: combining MAO inhibitors with serotonergic drugs and supplements such as SSRIs, SNRIs, tryptophan or 5-HTP can cause serotonin syndrome, and that risk should be assumed here. Some users also report sensitivity to sunlight, which has not been studied. Long-term safety is unknown.
8. Dihexa: The Most Potent in the Lab, With No Human Trials
Dihexa (PNB-0408) was developed from angiotensin IV by Joseph Harding and colleagues at Washington State University. In a 2013 paper (McCoy et al., Journal of Pharmacology and Experimental Therapeutics), it was about seven orders of magnitude, roughly 10 million times, more potent than BDNF at promoting new connections between neurons in a cell-culture assay. That figure comes from a dish, and potency in a dish does not translate into effects in a living brain.
In rats, Dihexa reversed memory deficits caused by the drug scopolamine and improved spatial learning in aged animals, and it is orally active and reaches the brain. There are no human trials of any phase.
How It Works
A follow-up study from the same group (Benoist et al., Journal of Pharmacology and Experimental Therapeutics, 2014) found that Dihexa binds hepatocyte growth factor (HGF) and boosts signalling through its receptor, c-Met, which helps form and maintain synapses.
HGF/c-Met is also a well-known cancer pathway: overactive c-Met signalling drives the growth and spread of many types of tumour. No study has shown that Dihexa causes cancer, but none has tested its long-term safety either, and this is the main theoretical concern.
Doses
No human data. There is no studied human dose, oral or topical, and the doses posted online are not based on human studies. Nothing about Dihexa’s effects or safety in people is known from trials.
How to Choose the Right Compound
These compounds are not interchangeable, and for most of them the evidence cannot tell you whether they will help you. What it can tell you is how much is known, and that is the most useful way to compare them.
If you’re new to nootropics
Piracetam is the best-documented starting point: the longest safety record, the most human data and the most predictable profile. Any effect takes weeks rather than days, and expect subtle effects at best, since trials in healthy adults have not shown reliable benefits.
If memory and learning are the goal
Pramiracetam and Noopept are the usual next options. Both rest on small, older trials in people with cognitive problems, and neither has strong evidence in healthy adults.
If focus for analytical work is the goal
Oxiracetam is the compound users most often name for technical work. That rests on user reports rather than trials in healthy people.
If anxiety or overstimulation is a concern
Fasoracetam is the racetam users mention for calmer focus, but its effect on anxiety has not been studied in people. Persistent anxiety is worth raising with a doctor.
If low motivation is the problem
9-Me-BC is discussed for this, but it has no human data and real interaction risks from MAO inhibition. Low motivation that lasts for weeks can be a symptom of depression, which has effective, approved treatments.
NSI-189 and Dihexa
NSI-189 has been studied only in depression, and its main trial missed its primary endpoint. Dihexa has no human data. Neither has any evidence as a cognitive enhancer in healthy people.
Legal Status in the US
None of the eight compounds is approved by the FDA for any use. They do not qualify as dietary ingredients, so products selling them as supplements are not legal; the FDA does not consider piracetam a dietary ingredient, for example. In practice they are sold online as research chemicals “not for human consumption”, which means no regulator checks what is in them, and testing of cognitive-enhancement supplements has found unlisted and wrongly dosed racetams.
Outside the US the picture differs: piracetam is a licensed medicine in a number of European countries, and Noopept is registered as a medicine in Russia. Rules vary by country, so check local law before buying anything.
Sourcing: What to Ask For
If you research these compounds, the biggest practical unknown is what is actually in the container. Ask the seller for a certificate of analysis for the specific lot you would receive, check that it comes from an independent lab and that the lot number and test date match, and remember that a certificate does not show that a compound is safe or effective.
SwissChems, a Muscle & Brawn partner, sells nootropics alongside its peptides and SARMs. It publishes a purity specification on its listings and states that batches are third-party tested, but lot-matched certificates are supplied on request rather than published for every product, so ask for the certificate for your lot before you order. Our SwissChems review covers its testing, pricing and the FDA warning letter it received in December 2024. The current partner code and discount are on our SwissChems brand page.

Pros
- Exceptional purity & testing (≥98%)
- Pharmaceutical-style packaging for stability
- Broad catalog across peptides & nootropics
- Strong reputation & consistency across years
Cons
- Some items frequently out of stock due to high demand
- Limited long-term data for some compounds
The Bottom Line
Racetams and nootropics are not interchangeable, and most of the confident claims made about them run well ahead of the human evidence.
- Piracetam has the deepest human record, with mixed results in cognitive impairment and little proof of benefit in healthy adults; pramiracetam, oxiracetam and Noopept rest on smaller, older trials.
- NSI-189 was tested in depression, missed its Phase 2 primary endpoint and has never been shown to grow brain tissue in people; fasoracetam’s ADHD signal comes from one small early trial.
- 9-Me-BC and Dihexa are cell and animal data only, with no studied human dose and unknown long-term safety.
- None of the eight is FDA-approved or legal as a supplement in the US; anyone researching them should ask for a lot-matched certificate of analysis first.
Frequently Asked Questions
Disclaimer
Please read carefully
The information on this site is for educational and informational purposes only, and is not medical advice. Always consult a qualified healthcare professional before using any supplement or medication, or making changes to your health, fitness, or nutrition routine.
Not medical advice
Content here is not a substitute for professional medical advice.
Consult your doctor
Talk to your doctor before starting any supplement or new routine.
Use at your own risk
We are not responsible for adverse effects from acting on this.
Do your research
Make informed decisions about your own health.
No guarantees
Individual results vary. No claims about outcomes.
Important — Never disregard professional medical advice or delay seeking it because of something you read here. If you think you may have a medical emergency, call your doctor or your local emergency number right away.




