

Contents9 sections
Oral anabolic steroids are synthetic derivatives of testosterone, made to work when swallowed instead of injected. They have been part of bodybuilding for decades, and their appeal has always been convenience: no needles and short courses. The practical question is whether they actually work for cutting and bulking, and whether the tradeoffs are worth it.
The short answer is that some do, for different reasons. Dianabol and Anadrol add weight fast, partly as water, which suits a bulk. Anavar and Winstrol do not convert to estrogen and are better known for holding on to muscle in a calorie deficit. All of them share the same core problem: the chemical change that lets them work by mouth also makes them harder on the liver and on cholesterol.
This article covers what the clinical research shows about the main oral steroids, how they compare for bulking and cutting, and where the evidence runs out.
Key Takeaways
- Most oral steroids are 17-alpha-alkylated, a change that lets them survive the liver after being swallowed. The same change makes them harder on the liver and on cholesterol than injectable testosterone.
- Methandrostenolone (Dianabol) and oxymetholone (Anadrol) produce the fastest weight and strength gains, which is why they are used to bulk. Much of the early gain is water; with Dianabol it is estrogen-driven fluid held outside the muscle cells.
- Oxandrolone (Anavar) and stanozolol (Winstrol) do not convert to estrogen. Oxandrolone improved lean mass or muscle protein balance in trials in burn patients, people with HIV-associated weight loss and older men, which is why both are linked with cutting.
- In 2023 the FDA withdrew approval of oxandrolone over risks that included liver problems and harmful blood lipid changes. In a 1989 JAMA study, stanozolol cut HDL cholesterol by about a third in six weeks.
- All oral steroids suppress natural testosterone. Most of the evidence comes from patients on medical doses for a few weeks, not from healthy lifters taking higher doses without supervision.
What Are Oral Anabolic Steroids?
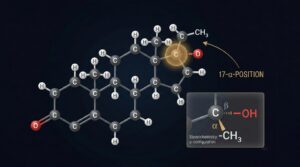
Oral anabolic steroids are synthetic compounds derived from testosterone. Most are modified at the 17-alpha position of the steroid molecule. This change, called 17-alpha alkylation (17-AA), slows their breakdown in the liver, so enough of the drug reaches the bloodstream after it is swallowed. A few oral steroids work differently, such as methenolone acetate and oral testosterone undecanoate, but the compounds bodybuilders mean by “orals” are almost all 17-AA.
Like all anabolic steroids, they bind to the androgen receptor in muscle and other tissues, which raises muscle protein synthesis and nitrogen retention. Whether a given oral fits a bulk or a cut depends mostly on two traits: whether it converts to estrogen (aromatizes), which drives water retention, and how androgenic it is.
The orals studied and discussed most are methandrostenolone (Dianabol), oxymetholone (Anadrol), 4-chlorodehydromethyltestosterone (Turinabol), oxandrolone (Anavar) and stanozolol (Winstrol). Each has a distinct profile.
Oral Anabolic Steroids for Bulking: What the Research Suggests
Bulking is a calorie-surplus phase aimed at gaining as much muscle and strength as possible. Several oral steroids have been studied in this context, and the evidence points to meaningful but mechanism-dependent results.
Many of the early controlled studies of steroids in strength-trained men used methandrostenolone. A 2004 review of this research in athletes by Hartgens and Kuipers, published in Sports Medicine, concluded that anabolic steroids can increase body mass, lean mass and strength, mainly at doses above medical replacement and in men who were already training. It also found that side effects on blood lipids and the liver were common.
Methandrostenolone (Dianabol)
Methandrostenolone (also called methandienone) is one of the oldest oral steroids. It promotes nitrogen retention and protein synthesis and is known for fast gains in body weight and strength within a few weeks.
A large share of that early weight is water. Methandrostenolone converts to a potent estrogen, 17-alpha-methylestradiol, and estrogen-driven fluid retention sits mainly outside the muscle cells, as extracellular water. That is what produces the smooth, full look, and much of it is lost once the drug is stopped. Dianabol is effective for raw mass but a poor fit for anyone after lean, dry gains. Estrogenic side effects such as gynecomastia are also more likely than with the non-aromatizing orals.
Oxymetholone (Anadrol)
Oxymetholone is one of the most potent oral steroids. It was developed to treat anemia and is still FDA-approved, as Anadrol-50, for anemias caused by poor red blood cell production. It was later tested in muscle-wasting conditions.
The best-known trial is a 16-week, double-blind, placebo-controlled study in people with HIV-associated wasting (Hengge and colleagues, published in AIDS in 2003). Oxymetholone increased body weight and body cell mass compared with placebo, but rises in liver enzymes were a clear safety problem, more so at the higher of the two doses tested.
Oxymetholone is a DHT derivative and does not aromatize, yet water retention and gynecomastia are commonly reported with it. The reason is not fully settled. Like the other orals here, it is 17-AA, and its label carries a boxed warning about peliosis hepatis (blood-filled cysts in the liver), liver tumors and blood lipid changes. For how it compares with another potent oral, see our Superdrol vs Anadrol breakdown.
Turinabol (4-Chlorodehydromethyltestosterone)
Turinabol was developed by Jenapharm in East Germany and became the most widely used drug in the East German state doping program, which Franke and Berendonk documented in Clinical Chemistry in 1997. It is a chlorinated form of methandrostenolone. The chlorine stops it converting to estrogen, so it causes far less water retention than Dianabol, and it is less androgenic.
Controlled human data on Turinabol is thin. Its reputation for slower, leaner gains comes mostly from user reports, which is why it is discussed for both bulking and cutting. It is still 17-AA and carries the same liver and cholesterol concerns. Our Turinabol cycle guide covers what users report and what the risks are.
Oral Anabolic Steroids for Cutting: Preservation Over Growth
A cutting phase is a calorie deficit aimed at losing fat while preserving lean muscle tissue. A deficit is catabolic: the body breaks down some muscle for energy along with fat. Anabolic steroids can counter this by keeping protein balance positive even when calories are low.
Not every oral suits this role. Those that cause water retention hide the visual progress a cut is meant to show. The orals most often studied for preserving lean tissue are the ones that do not aromatize.
Oxandrolone (Anavar)
Oxandrolone is the most studied oral steroid for preserving lean tissue. It does not convert to estrogen, causes little water retention and is mildly androgenic. Its clinical record comes from catabolic patients. In severely burned patients, a randomized trial found it improved muscle protein balance (Hart and colleagues, Annals of Surgery, 2001), and it was also studied in HIV-associated weight loss.
In healthy older men, trials by Schroeder and colleagues found that 20 mg a day for 12 weeks increased lean mass and reduced total and trunk fat. These are the results usually quoted in favor of Anavar for cutting, but the people studied were patients or older adults on medical doses, not lean lifters in a planned deficit.
In 2023 the FDA withdrew approval of oxandrolone products in the US. It concluded that the drug’s benefits no longer outweighed its risks, which include liver problems such as peliosis hepatis and liver tumors, and harmful changes in blood lipids. Bodybuilders commonly pair oxandrolone with testosterone; our test and Anavar cycle guide covers that combination.
Stanozolol (Winstrol)
Stanozolol is a DHT-derived oral with no estrogenic activity. In medicine it was used to treat hereditary angioedema, a rare swelling disorder, and it is no longer marketed in the US. Because it causes no estrogen-driven water retention, it is popular in cutting phases and contest prep, where a dry, defined look is the goal. Users commonly report joint aches on it.
Its effect on cholesterol is among the worst documented. In a 1989 study in JAMA, Thompson and colleagues gave men either 6 mg a day of oral stanozolol or 200 mg a week of injectable testosterone enanthate for six weeks. Stanozolol lowered HDL cholesterol by about a third and raised LDL; testosterone lowered HDL far less.
Comparing Effectiveness: Bulking vs. Cutting Use Cases
No oral steroid works in isolation from diet, training volume, dose and the person’s own hormone levels. With that caveat, the main orals sort roughly like this:
| Compound | Converts to Estrogen | Water Retention | Usual Reported Use | US Medical Status |
|---|---|---|---|---|
| Methandrostenolone (Dianabol) | Yes | High | Bulking | No longer approved |
| Oxymetholone (Anadrol) | No, but estrogen-like side effects are reported | High | Bulking | Approved for certain anemias |
| Turinabol | No | Low | Lean gains, either phase | Never approved |
| Oxandrolone (Anavar) | No | Low | Cutting, recomposition | Approval withdrawn in 2023 |
| Stanozolol (Winstrol) | No | Low | Cutting, contest prep | No longer marketed |
Dianabol, and Anadrol with its estrogen-like effects, produce the most dramatic changes on the scale during a bulk. Much of that is water, which hides muscle quality and leaves when the drug stops. Oxandrolone and stanozolol are linked with cutting and recomposition, but their absolute muscle-building effect is more modest. Our guide to steroid cycles for lean mass covers how water weight distorts results.
Orals are rarely the main mass builder. They have short half-lives, and their strain on the liver limits how long they can be run, so they are usually taken in short courses or added to an injectable testosterone base. The 17-AA orals also tend to harm cholesterol more than injectable testosterone, as the stanozolol study shows. Whether an oral is “effective” depends on the goal and on how much risk someone is willing to take.
Safety Considerations and Research Limitations
Liver
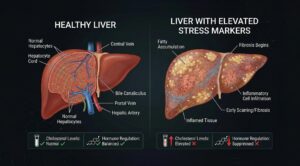
The 17-alpha alkylation that makes oral steroids work also makes them harder on the liver. Documented problems include raised liver enzymes, cholestasis (blocked bile flow, which can cause jaundice), peliosis hepatis and liver tumors, mostly with high doses or long use. This is one of the main reasons clinical use of these drugs is time-limited, and it is part of why the FDA withdrew oxandrolone.
Cholesterol and Heart Risk
Oral steroids lower HDL cholesterol (the protective form) and raise LDL, a pattern linked to higher cardiovascular risk over time. These lipid changes are consistently larger with oral 17-AA steroids than with injectable testosterone, as the 1989 stanozolol study showed. Stacking two orals, or running them for longer, is unlikely to make this better.
Testosterone Suppression and Recovery
Any anabolic steroid, oral or injected, signals the hypothalamic-pituitary-gonadal axis to cut natural testosterone production. Recovery after stopping is slower and less certain than many cycle guides suggest. In a 2023 study of 641 men seen at a UK clinic after stopping anabolic steroids, only 48% had fully recovered their reproductive hormones, and men who had used more compounds were less likely to recover.
Post-cycle therapy (PCT) with tamoxifen or clomiphene is commonly used to try to restart natural production. Neither drug is approved for this use, and the evidence for PCT is limited. Blood work before and after is the only way to know where recovery stands.

 SERMs & AIs
Overview
- Form: Oral Capsules
- Dosage: 25-40 mg daily for PCT or for gyno flare-ups
- Typical Cycle: 4-6 weeks
- Cost: $81.95
- Stacking Options: Higher testosterone doses or post-cycle recovery
Pros
- Large mortality benefit in ER-positive breast cancer; five years of adjuvant treatment cuts recurrence roughly by half and breast cancer mortality by about a third, with the effect persisting well past the treatment period
- Works in premenopausal and postmenopausal women alike, unlike aromatase inhibitors, which makes it the default for younger patients
- Bone-protective in postmenopausal women, since it acts as a partial estrogen agonist in bone — the reverse of anastrozole's main liability
Cons
- Endometrial hyperplasia and a two-to-three-fold increase in endometrial cancer risk in postmenopausal women, requiring investigation of any abnormal bleeding
- Elevated risk of venous thromboembolism and pulmonary embolism, particularly around surgery or immobility
- Hot flashes, vasomotor symptoms and mood effects are common; CYP2D6 status and strong inhibitors such as certain SSRIs can reduce conversion to the active metabolite
SERMs & AIs
Overview
- Form: Oral capsules (25 mg each, 60 capsules)
- Researched Dosage: 25 mg to 50 mg daily for PCT
- Typical Cycle: 4-6 weeks
- Cost: $69.95
- Stacking Options: Tamoxifen, HCG, Enclomiphene
Pros
- A SERM that blocks estrogen at the hypothalamus, prompting the body to make more LH, FSH and its own testosterone.
- Studies in men with low testosterone found it raised testosterone while preserving sperm production, unlike TRT.
- It is oral, inexpensive and has been in medical use since 1967, so its effects are well documented.
Cons
- About a third of each dose is zuclomiphene, a long-lasting isomer linked to mood swings, irritability and low mood.
- Blurred vision, floaters and light sensitivity have been reported; visual symptoms are a reason to stop.
- It is FDA-approved only for female infertility, so use in men is off-label, and this product is sold for research use only.
What the Research Does Not Tell Us
Most research on oral steroids comes from clinical populations, such as burn patients, people with HIV-associated wasting, anemia patients and older men. They were given medical doses, usually for a few weeks to a few months, under supervision. Healthy lifters often take higher doses, stack several compounds and do so without monitoring. The long-term risks of that kind of use remain poorly studied.
Oral anabolic steroids are Schedule III controlled substances in the United States and are controlled in many other countries. All are prohibited in sport by WADA. This article does not advocate their use outside legitimate medical supervision.
The Bottom Line
Oral steroids can work for both bulking and cutting, but different compounds work for different reasons, and every one of them trades convenience for liver and cholesterol risk.
- Dianabol and Anadrol add weight fastest, but much of it is water. With Dianabol it is estrogen-driven extracellular fluid that leaves when the drug stops.
- Anavar and Winstrol do not aromatize and are linked with holding muscle in a deficit, but their muscle-building effect is modest, both lower HDL cholesterol, and the FDA withdrew oxandrolone in 2023.
- Most of the evidence comes from patients on medical doses, not healthy lifters on higher doses. All orals suppress natural testosterone, and full recovery after stopping is far from guaranteed.
Frequently Asked Questions
Disclaimer
Please read carefully
The information on this site is for educational and informational purposes only, and is not medical advice. Always consult a qualified healthcare professional before using any supplement or medication, or making changes to your health, fitness, or nutrition routine.
Not medical advice
Content here is not a substitute for professional medical advice.
Consult your doctor
Talk to your doctor before starting any supplement or new routine.
Use at your own risk
We are not responsible for adverse effects from acting on this.
Do your research
Make informed decisions about your own health.
No guarantees
Individual results vary. No claims about outcomes.
Important — Never disregard professional medical advice or delay seeking it because of something you read here. If you think you may have a medical emergency, call your doctor or your local emergency number right away.




